SKIP NAVIGATION
MyChart Search
Wellstar Go Back
MyChart
  • Find a Doctor
  • Locations
  • Medical Services
    Popular Services
    • Emergency Care
    • Urgent Care
    • Virtual Care
    • Primary Care
    • Women's Health
    • Pediatric Care
    • Cancer Care
    • Heart Care
    • Neuro Care
    • Orthopedics
    • View All Medical Services
    Expanded Services
    • Lab Services
    • Imaging
    • ENT
    • Pulmonary
    • Gastroenterology
    • Urology
    • Physical Therapy
    • Behavioral Health
    • Pharmacies
    • View All Medical Services
    For Providers
    • Refer a Patient
    • Transfer a Patient
    • Physician Relations
    • Wellstar Clinical Partners
    • Provider Resources
  • Patient Resources
    Patient Portal
    • MyChart Login
    • Sign-Up for MyChart
    • Get Medical Records
    Visiting
    • Visitation Guidelines
    • Patient Guides
    • Find My Way
    Billing & Insurance
    • Accepted Insurance
    • Pay Your Bill
    • Financial Assistance
  • Wellstar for You
    Community
    • Classes and Events
    • Center for Health Equity
    • Support Groups
    • Community Outreach
    • Wellstar Find Help
    • Translation Services
    • Volunteer Opportunities
    Health Content
    • Articles
    • PeopleCare
  • Find a Doctor
  • Locations
  • Medical Services
  • Patient Resources
  • Wellstar for You

Popular Services

Emergency Care Urgent Care Virtual Care Primary Care Women's Health
Pediatric Care Cancer Care Heart Care Neuro Care Orthopedics

Expanded Services

Lab Services Imaging ENT Pulmonary Gastroenterology
Urology Physical Therapy Behavioral Health Pharmacies View All Medical Services

For Providers

Refer a Patient Transfer a Patient Physician Relations Wellstar Clinical Partners Provider Resources

Patient Portal

MyChart Login Sign-Up for MyChart Get Medical Records

Visiting

Visitation Guidelines Patient Guides Find My Way

Billing & Insurance

Accepted Insurance Pay Your Bill Financial Assistance

Community

Classes and Events Center for Health Equity Support Groups Community Outreach
Wellstar Find Help Translation Services Volunteer Opportunities

Health Content

Articles PeopleCare
  • Home
  • Articles
  • Stroke prevention and the future of stroke care
Article Category: Highlights

Stroke prevention and the future of stroke care

Republished with permission of the Atlanta Business Chronicle

Published on May 29, 2025

Last updated 03:43 PM May 29, 2025

An artistic representation of stroke experts inspecting a brain with a magnifying glass.

This article was originally published on Atlanta Business Chronicle on May 19, 2023.

Stroke is the fifth leading cause of death in the United States. The Georgia Department of Public Health reports the state had the 12th highest stroke death rate in the country. Georgia is also part of the “stroke belt,” an area of the southeastern United States with stroke death rates 30% higher than the rest of the nation.

As the leading — but preventable — cause of disability, stroke can happen at any age.

Stroke is a medical emergency, meaning the blood flow to an area of the brain is cut off, depriving brain tissue of oxygen and nutrients. When this happens, brain cells start to die and abilities controlled by that area of the brain, such as speech or muscle control, are lost.

New drugs and new advanced treatments — such as the Tigertriever and Artemis — are helping reduce the death and disability impact of stroke, as well as comprehensive care programs and innovative hospital partnerships that expand stroke services into rural areas.

Physicians from Wellstar Health System and the CEO of a hospital in northeast Georgia joined Atlanta Business Chronicle to discuss stroke prevention and the future of stroke care.

Panelists & moderator

  • Dr. Rishi Gupta, Endovascular Neurologist and Co-Medical Director of Neuro Care
  • Dr. Ashis Tayal, Vascular Neurologist, Wellstar, Director of Neuro Care Network
  • Van Loskoski, CEO, Stephens County Hospital
  • David Rubinger, Market President & Publisher, Atlanta Business Chronicle; Moderator

Pictured: headshots of the panel of experts from Wellstar Health System and the CEO from a rural Georgia hospital discussing advances in stroke care.

What is stroke, screening and secondary prevention

David Rubinger: Dr. Tayal, set the stage for us about the definition of stroke.

Dr. Ashis Tayal: A stroke is a sudden injury of the brain due to blockage or rupture of an artery in the brain. Injuries to the brain and disability can vary significantly.

The most common, ischemic stroke injury, is due to obstruction of an artery that causes a loss of blood flow to a critical part of the brain which damages the brain rapidly.

The other type of stroke is hemorrhagic stroke, where there’s a rupture of an artery, bleeding into the brain, or the surfaces of the brain, and that is called an intracerebral hemorrhage or a subarachnoid hemorrhage.

Rubinger: I think Americans have become a little better educated as to who’s at risk for stroke, but why don’t you walk us through that. Who would be a potential stroke candidate?

Tayal: High blood pressure, or hypertension, is the most common risk factor for both ischemic and hemorrhagic strokes. High blood pressure is an extremely common but controllable condition. Almost 80% of people have hypertension as they’re getting older.

Other risk factors include diabetes associated with elevated blood sugars causing accelerated blockage of arteries and high cholesterol, which can be related to diet and genetics.

Atrial fibrillation, a common heart arrhythmia that occurs as people get older, also places people at risk for the most severe and disabling types of strokes. And plaque buildup in specific arteries of the neck and brain also leads to an increased risk of stroke.

Smoking is another risk factor. Many adults still smoke despite a lot of progress in stroke treatment, and smoking puts people at risk for different types of stroke.

Rubinger: What about atmospheric things like stress and other areas like that? How does that play into it? Or do those things manifest themselves because of the other underlying physical conditions?

Tayal: I don’t view stress, in and of itself, as a risk factor for stroke. I think that’s more related to people’s environments and their own personalities and how they respond to stress. I do think people who are under undue stress can have poor lifestyle habits, and those poor lifestyle habits, whether poor eating habits, smoking, weight gain or lack of exercise, can lead to conditions that increase the risk for stroke.

Rubinger: So how is the healthcare system doing treating strokes? Do you believe that what’s going on at the primary care provider’s office is helping or do we have a way to go?

Tayal: In the United States, preventive care has improved the treatment of risk factors that lead to stroke, but communities must maintain routine checkups as many of the risk factors are silent.

There are improved treatments for hypertension, more aggressive treatment for diabetes, and more efforts at smoking cessation. Just the fact that we treat hypertension better than we did a generation ago has had a great impact on lowering the prevalence of stroke.

That being said, some of the most exciting work on stroke has often been done in the area of acute treatment of stroke with clot-busting drugs, catheter-based treatments and medications to protect the brain during an acute injury.

Rubinger: Has pharmacology gotten better in terms of the hypertension medicines that are out there? Have anti-cholesterol medicines improved in recent years?

Tayal: In the past, healthcare providers were often undertreating people with hyperlipidemia — high cholesterol — and not fully appreciating the benefits of significant reductions in cholesterol levels. For example, we’ve learned that driving cholesterol down into much lower ranges under 55 mg/dL can benefit our patients who have vascular disease as a cause for their stroke.

In the fight against high cholesterol, newer medications that prevent the absorption of cholesterol are now available. Recent developments have led to the discovery of a new underutilized class of drugs called PCSK-9 inhibitors that are highly effective.

One exciting development is the ability to emulate what cardiologists have been doing for the heart without open heart surgery. Now we’re able to insert tiny catheters into the femoral artery, which is a small artery in the leg, and trace it with X-rays up through the body to the brain to remove blood clots.

- Dr. Rishi Gupta

Endovascular Neurologist & Co-Medical Director of Neuro Care

Advanced treatments

Rubinger: Dr. Gupta, we were talking about more of the preventive side of things, but you get to work in the advanced treatment area. It is amazing what’s happened in my lifetime. When you have a stroke patient and treat them quickly, is recovery more possible now than in the past? What are the advanced treatments that make you feel good about the work you do?

Dr. Rishi Gupta: We’re in the heart of what’s called the stroke belt, where the prevalence of stroke is very high and the population presenting to the emergency room is also younger. It’s unfortunate to see the impact on younger families when the patient may be the sole source of income for the family. The toll it takes financially, physically and emotionally is tremendous. It’s important to understand the impact, stress and burden families feel after their loved one suffers a stroke.

When Ashis and I were in training, we were discouraged from going into stroke treatment because we were told all we would be able to do is give the patient an aspirin a day and send them to rehab.

Now, the range of treatments is much broader and more effective. Treatments have exponentially increased. And the fact that stroke fell to the fifth leading cause of death from the third in a decade speaks to the effectiveness of these treatments. We are absolutely making a dent in stroke death and injury.

One exciting development is the ability to emulate what cardiologists have been doing for the heart without open heart surgery. Now we’re able to insert tiny catheters into the femoral artery, which is a small artery in the leg, and trace it with X-rays up through the body to the brain to remove blood clots.

As of 2015, that treatment has been shown to be highly effective at reducing not only mortality, but disability. Almost 50% of patients who get that treatment can return to a normal functioning life.

Before, that number was closer to 20%. That’s an astounding achievement for stroke care.

The second thing is not only going after big clots but being able to go after small clots. That’s another subset of the population we can now treat which we couldn’t treat before. Catheter-based technologies have been an innovative step forward for our field.

Recently, Wellstar’s Neuro Care team tested a groundbreaking device to treat complex ischemic strokes, working alongside UCLA’s Dr. Jeffrey Saver and device manufacturer Rapid Medical. The technology is called Tigertriever, and it’s adjustable. It allows our specialists to remove the blood clot and restore blood flow with much greater control and precision. The device is now available at hospitals across the United States.

We also helped test a cutting-edge device for treatment called Artemis. Doctors insert a neuroendoscope — a small tube with a camera — into the brain to reach the bleeding in areas that were previously unreachable.

Rural health

Rubinger: You hear about struggles in rural areas when it comes to healthcare. Stephens County Hospital in Toccoa, Ga., is a rural hospital and an example of disparities in healthcare between urban and rural areas. Van, what are the challenges you face in your community when it comes to access to advanced stroke care? And what are the benefits of having doctors like Drs. Gupta and Tayal available to you to help serve your population?

Van Loskoski: Access is the leading challenge for rural healthcare systems.

There’s a significant lack in the availability of highly trained clinical staff, particularly with access to specialty physicians.

Most doctors complete their training in large hospitals in metropolitan areas and remain in that type of setting for the entirety of their careers. There are certainly programs that offer financial incentives for physicians to work in rural areas, typically in the form of student loan forgiveness. But what we often see is that physicians will move to a rural area only for an amount of time required to meet the obligation for that debt forgiveness and they often move back to larger cities.

Rural physicians don’t have as many resources readily available to them as those in larger facilities in urban areas.

It’s also hard for smaller communities like ours to financially support some of these specialists. That isn’t to say the need isn’t there. However, the case volume might be lower, so for stroke services, we aren’t able to support having a team of endovascular neurologists on site. The challenge is finding a way to bring that service here when we need it in a cost-effective manner.

I’m a firm believer that one reason rural community hospitals fail or struggle is that they fail to meet the needs of the community they serve.

So often we see hospitals in rural areas cutting services in efforts to save money, but you can only carve out so much before you’ve eventually carved out your purpose.

Urban-rural hospital partnership

Rubinger: The need for advanced stroke care in rural areas has been proven. I believe a 2020 study published in the American Heart Association Stroke Journal found rural patients with stroke were less likely to receive intravenous thrombolysis or endovascular therapy and had higher in-hospital mortality than their urban counterparts. How have findings like that influenced your decisions at Stephens County Hospital?

Loskoski: We’re focused on the expansion of stroke care in a cost-effective and innovative way. That’s where Dr. Tayal, Dr. Gupta and the rest of the Wellstar team come into play. Telemedicine represents a big opportunity for rural hospitals that haven’t leaned into the utilization of tech in the past. The pandemic propelled us forward in the adoption of telemedicine by clinicians and patients. Now patients are more comfortable using telemedicine, which allowed us to tie into the resources that existed at Wellstar Kennestone.

That’s something that can really benefit our patients.

Rubinger: Van, before we hop into the details of telemedicine, tell me about how your hospital and Wellstar came together. Did it take a certain degree of salesmanship for you to convince the hospital leadership or the authority that governs your hospital to fall into line with this?

Loskoski: Our board saw the need for us to progress as a system in terms of what services we were offering, and focus on retaining more patients here. I came in with that challenge, the board already having identified that was the direction we needed to take.

The relationship with Wellstar was just as natural. I reached out to a contact at Wellstar and said, “Looking at Toccoa’s population health needs, stroke is really high up on the list.” And he said, “Well, let me just put you in touch with our stroke team.” A month later, I’m meeting Dr. Tayal at Wellstar Kennestone and he’s saying “We can do this. We are ready and we’re excited.”

It was a really warm reception and we saw the mutual benefit. We were bringing needed services to our community, and Wellstar would be able to utilize their resources to support other Georgia communities.

Rubinger: Dr. Tayal, from your standpoint, what was going on within Wellstar’s world? You saw this opportunity for telemedicine to help expand your reach into these rural communities. How does Wellstar view it and what are the challenges you face when doing this? You may not face any. Tell me about how that whole relationship works.

Tayal: There was an opportunity to further develop Wellstar telestroke services with our team of seven vascular neurologists and our network of hospitals. We were able to improve how the telestroke program operates day-to-day so that the telestroke service is highly reliable, consistent and delivers a valuable service to patients.

With the aid of technology, we could evaluate patient symptoms, review brain images and recommend stroke treatment in rural communities and hospitals such as Stephens County Hospital.

So the timing was very good because we had the physicians and we had developed the processes of care.

Rubinger: Walk us through how telestroke actually works. The scenario is, Van’s hospital has a patient who presents with the onset of a stroke. Walk me through the process here. What happens?

Tayal: When a person with suspected stroke within the last 24 hours arrives at Stephens County Hospital — the emergency room physician is connected with the on-call vascular neurologist at Wellstar within 1-2 minutes. The doctors at Wellstar and the physicians at Stephens County Hospital discuss the patient and their symptoms and decide quickly what kind of imaging should be done and which therapies might be appropriate. Then the Wellstar neurologist connects to a video conferencing system — a hardware and software platform that protects patient privacy and is designed to deliver telestroke consults. Virtual meeting software connects us to a video cart in the Stephens County emergency room to communicate directly with the patient, nurse and family members at their bedside.

Rubinger: Is this considered to be the initial triage or does the ER doctor typically have enough baseline knowledge to be able to administer TPA or do something really early on?

Tayal: This is the first evaluation. So, we’re rapidly examining the patient and judging the level of stroke disability and collecting information about their history. Software called Viz.ai allows for an artificial intelligence-driven automated processing of CT brain scan images that rapidly helps us in our decision-making, helps us identify a blood vessel blockage faster, helps us sort out who may be eligible for endovascular treatments. The telestroke provider can then speak to the patient as well as the consultant physician at Stephens County and make decisions about whether the patient is having a stroke or some other condition, whether the patient should receive the clot-busting medication and whether they should be transferred rapidly to another medical center for a more advanced treatment. We address all of the patient’s questions, and we’re trying to do all of this work in less than 20 to 30 minutes. It’s a very rapid workflow.

Rubinger: an, I assume the doctors who are on staff at Stephens, they appreciate that. I would think this gives them the additional tools that they maybe wouldn’t have at their disposal. Or are they like “oh wow, someone is coming in and looking over my shoulder at the work I should be doing?” What is the psychology of your staff?

Loskoski: This is something that we’ve really been asking for, “Give us the specialty support that we need so that we can keep more patients here in our hospital.” If you’re an ER physician or a hospitalist, you really take it personally when you have to transfer a patient to another facility because you know the burden that places on the patient and their family. For many in our community, traveling 45 minutes to an hour away is not a possibility.

I’ve seen it firsthand when it’s such a burden on patients to have their family members travel to visit them while they’re hospitalized. So, every one of our physicians has been extremely supportive and excited about this initiative.

The future of stroke care

Rubinger: r. Gupta, you get to play the role of taking out a crystal ball and talking about the future. It sounds like we’ve made great progress, but that there’s more still to come in terms of trials, devices. We started talking about AI and devices and technologies that are out there. What are the things that get you excited about the future of patient care?

Gupta: We’ve made a big dent in stroke, and I think the part we have not really been able to catch up with is rural health. I believe the future is equalizing outcomes in rural communities to those in metropolitan communities. Step one to make that happen is telestroke.

The most exciting technology is robotics, where we will remotely deliver endovascular catheter-based surgeries in rural communities. It sounds sci-fi today, but one can imagine where a few hospitals in select rural communities are identified as high-volume centers where stroke patients can be transported.

Physicians like Dr. Tayal will evaluate a rural patient through telestroke and alert an endovascular surgeon that this patient has a clot. The patient would go to their local facility’s cath lab and endovascular surgeons would perform remote thrombectomy and remove the clot. In this partnership scenario, the rural hospital would have an endovascular technician. The hospital would not necessarily need a neurointerventional physician on site.

We could do this remotely, understanding that every minute, we’re losing hundreds of thousands of neurons. If we can remove the clot, then you can transfer the patient if necessary.

That sounds crazy in itself. But to take it one step further, consider if EMS now has been tooled with artificial intelligence technology to detect how bad the stroke is. Imagine an application where the first responder’s smartphone takes a picture of the patient’s face, and it says, “that’s a big stroke.” Then EMS can drive just a few miles to a rural facility where that robot exists.

In the next five years, Georgia health experts could set up a road map that would give rural citizens access to the same technology that’s available in metropolitan cities. For me, that’s super exciting.

Rubinger: The American health care system is wonderful in many ways. But we’re a little slow to implement. Where are we in getting there and what’s slowing it down?

Gupta: Physicians need to learn the skill set and get comfortable with the technology. Robotics is a very different skill than using your hands. We’re doing carotid stent procedures which are stents in the neck, as opposed to going into the brain, to refine our skills right now. And the technology from the robotic side of doing brain work is not quite “there” yet. Cardiologists can implant stents in the heart remotely today. India is leading this charge right now. They’ve demonstrated they can safely place stents in the heart remotely from a 30-mile radius.

Another challenge is the 5G network is required so there’s no downtime in the middle of a procedure. But I think the 5G network will be up and working nationwide in the next five years.

Learn more about stroke care at Wellstar. 
 

Tags

Rishi Gupta Kennestone Regional Medical Center North Fulton Medical Center
Paulding Medical Center Cobb Medical Center Douglas Medical Center Spalding Medical Center West Georgia Medical Center Neuro Care
Related Articles
Male and female head and neck cancer specialists stand together looking at a chart and discussing the best treatment for a complex case of head and neck cancer.

PeopleCare

Wellstar PeopleCare | Beating Cancer Twice with Coordinated Care

David Butler’s cancer journey began when he underwent treatment for an aggressive head and neck cancer. Supported by his family, faith and a team of head and neck cancer specialists, he had part of his jaw removed and went through radiation therapy and intense rehabilitation.

A major setback

The same year of his jaw surgery and initial radiation course, David’s recovery was beginning to feel like “smooth sailing.” Just as life started to feel manageable again, he faced an unexpected challenge.

David and his wife, Jill, got devastating news: routine follow-up imaging revealed three new tumors on the other side of his neck and tongue. Dr. Fiyin Sokoya, David’s cancer surgeon, removed lymph nodes from David’s neck, had them biopsied and confirmed that it was an aggressive cancer.

At first, David felt so discouraged that he didn’t want to move forward with treatment.

However, seeing that a group of experts were working together to give him the best, evidence-based treatment path for his unique circumstance gave him confidence to renew his fight against cancer.

Keep reading
David Butler stands, smiling, with Dr. Fiyin Sokoya, a dual board-certified head and neck cancer specialist and facial plastic surgeon at Wellstar.

PeopleCare

Wellstar PeopleCare | Moving Fast, Working Together: Advanced Head & Neck Cancer Surgery Keeps David Smiling

David Butler's cancer journey took him through a rare jaw reconstruction, radiation and coordinated care from specialists across Wellstar. His care team collaborated to provide what he needed as quickly and efficiently as possible.

A bothersome mouth sore

Lean and energetic, David is quick with a joke and even quicker with a smile. A neatly trimmed mustache frames a grin that lights up his blue eyes, illuminating his trademark optimism and humor. They’re qualities he kept intact throughout cancer treatment and draws on today, when he encourages people who are newly diagnosed with cancer.

It started with a sore on his gum in the fall of 2023. He assumed it would heal on its own. Instead, it got worse. When he could hardly swallow a few months later, his dentist referred him to an oral surgeon for a biopsy. That’s when he got the life-changing news: it was cancer.

“You hear the big C and it scares you to death,” David said. “But there's light at the end of the tunnel. There's always hope.”

What followed was cancer treatment involving surgery, radiation, chemotherapy and support from a whole team of cancer specialists. Along the way, David said he leaned on his faith, the support of his wife, Jill, who he credits as his biggest advocate—and the expertise of Wellstar caregivers.


David Butler grins standing next to his wife Jill, who he credits as his biggest advocate throughout treatment.
Keep reading
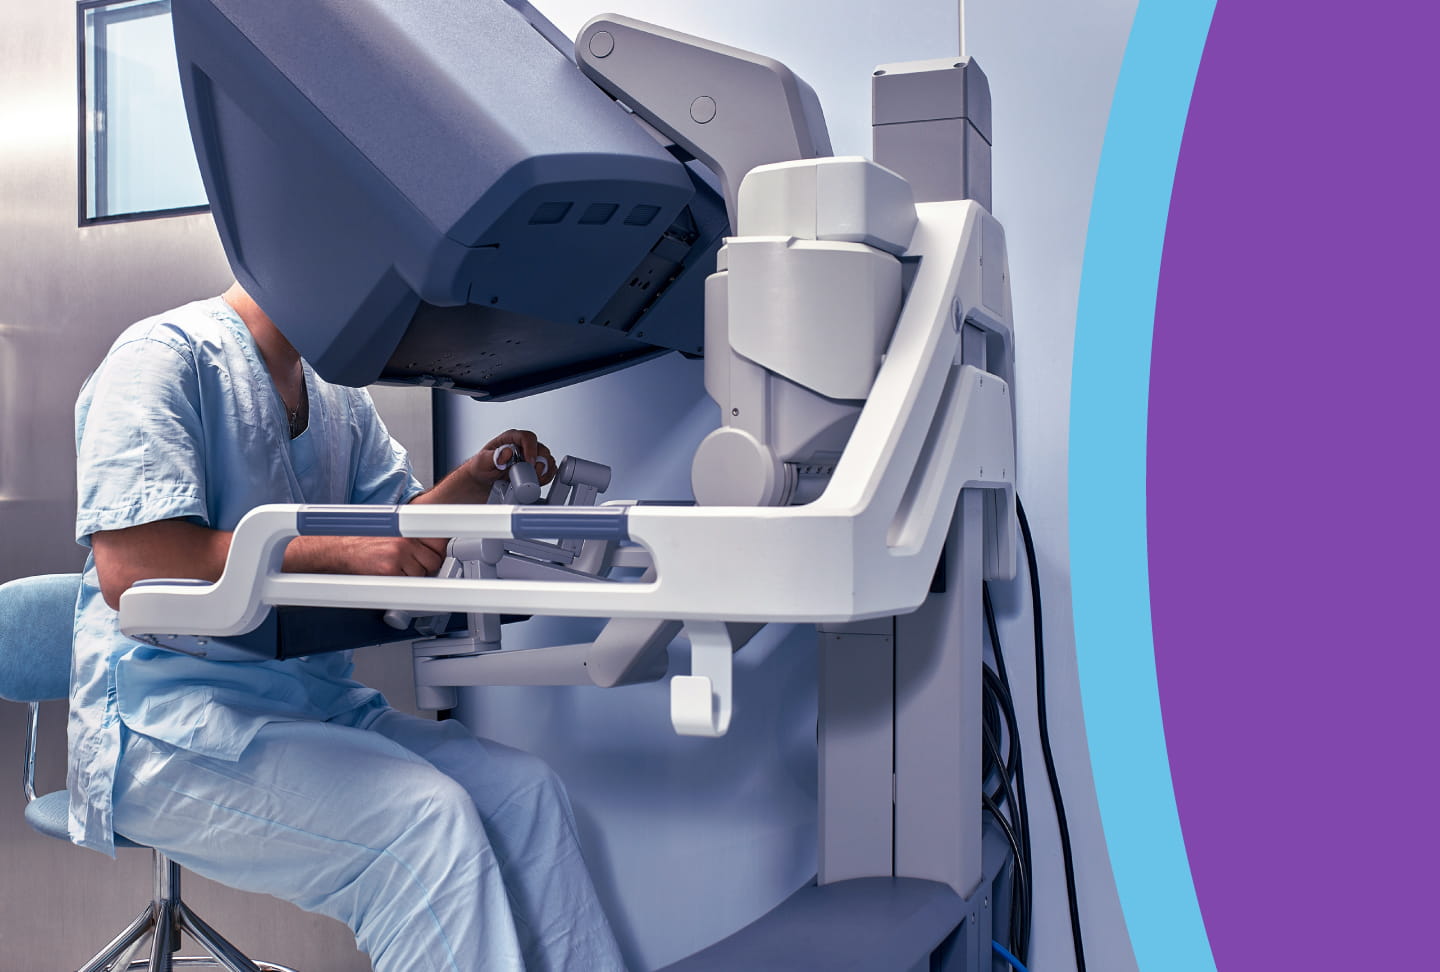
image of surgeon seated at robotic system console with hands guiding the controls

Highlights

Amazing Advancements—Robotics Expand Patient Care Options

Robotic surgery has transformed how surgeons care for patients with new innovations yet again. At Wellstar, continued investment in advanced technology is helping elevate surgical care across specialties—giving patients the option to have more precise and less invasive procedures that are easier to recover from.

“Technology continues to advance to provide newer and safer alternatives to treat our patients,” said Dr. Aaron Bolduc, a general surgeon at Wellstar MCG Health Medical Center. “As we adopt this new technology, we are able to lead the way in patient care with excellent outcomes.

Wellstar has expanded its robotic surgery program with the addition of the Da Vinci 5 robotic surgical system—also known as the DV5—at most locations, along with new applications for single-port surgery. These innovations build on years of robotic experience while helping clinicians deliver world-class care and train the physicians of the future.

Fast recoveries

The latest technologies continue to redefine what’s possible in surgery, including even shorter hospital stays and faster recovery timelines.

Dr. Jay Singh, Wellstar chief surgical officer and a colon and rectal surgeon, said significantly smaller incisions make a big impact: “That is potentially huge from the standpoint of patient satisfaction, decreased pain, quicker recovery time, a decrease in narcotics used and a quicker return to work.”

The impact is so great that some robotic procedures that previously required a few nights in the hospital are now being done as outpatient procedures, allowing patients to recover in the comfort of their homes.

DV5: A new level of precision

The DV5 represents a significant step forward in robotic surgery—notably for surgeon awareness and control. One of its most notable advancements is force feedback: “The ability to sense hard and soft tissue during robotic surgeries is a game changer,” said Dr. Julie Chang, an obstetrics and gynecology specialist. She was the first surgeon to use the DV5 system at Wellstar Cobb Medical Center.

“Surgeries will be even more precise and efficient with this tool, which will further reduce post-operative pain and make recovery time faster,” said Dr. Chang.

The machine’s sensory feedback means surgeons can apply the exact amount of pressure needed.

“The DV5 allows the surgeon to sense how much push-or-pull force they apply to delicate structures in the body,” said Dr. Fritz Jean-Pierre, a bariatric surgeon at Wellstar Kennestone Regional Medical Center. “Less strain means less trauma and potential injury, leading to faster patient recovery.”

Wellstar’s robotic program is grounded in decades of experience, combined with a commitment to adopt best‑in‑class technology.

“Having performed robotic surgery for well over 20 years, I started with the very first Da Vinci surgical robot,” said Dr. Scott Miller, Wellstar director of robotic surgical services and a urologist at Wellstar North Fulton Medical Center. “I was amazed when that came around, but I never cease to be amazed by every advancement. Now we have introduced the DV5 model to most Wellstar locations with 10,000 times processing power.”

With that comes enhanced visualization, instrument responsiveness and precision across a wide range of procedures.

“The DV5 is ideal for many urologic procedures, such as prostate and kidney removal, bladder surgery and urinary tract reconstruction,” Dr. Miller said. “The improved range-of-motion and visualization features help us protect healthy tissues and nerves.”

Keep reading

COMMUNITY CARE

Community Care
In the Community Health Highlights Events & Classes
For Business
Corporate Purchasing Community Health Needs Assesment
Give
Wellstar Foundation Donate Ways to Give Volunteer

ABOUT US

About Wellstar Diversity Equity Inclusion & Belonging Leadership Wellstar Board of Trustees Healthcare Innovation Safety First Commitment Wellstar Research Institute Latest News

CAREERS & EDUCATION

Careers at Wellstar Graduate Medical Education Pharmacy Residency

PATIENT RESOURCES

Pay Your Bill Accepted Insurance

HELP

Contact Us Hospital Transparency Information Price Transparency Policy and Privacy Information

MEDIA

Media Room

Copyright © 2026 Wellstar Health System. All Rights Reserved.

Wellstar does not discriminate on, exclude people or treat them differently on the basis of race, color, national origin, age, disability, sex, gender identity or expression or any other type of discrimination prohibited by law.

  • Internet Privacy Policy
Cookie Preferences

We use cookies for booking and general analytics. Learn more about or internet privacy policy.